Home › Will premiums go up in 2027?
Will Health Insurance Premiums Go Up in 2027? What Insurers Asked For, What States Approved, and What To Do Before December 15
Written and reviewed by Dick Tracy, licensed health insurance broker (NPN 20414610) · Published October 7, 2026 · Updated November 12, 2026

Quick answer Yes. For most people health insurance premiums go up in 2027, and the rates are now final in all 50 states plus DC. On the individual market the statewide averages run from 3.0 percent in Vermont and 6.0 percent in New York up to 27.9 percent in Arizona, with New Mexico, Montana, Alaska, Washington and South Carolina all above 22 percent. Nationally, KFF found the finalized benchmark silver premium is up 13 percent on average, after marketplace insurers asked for a median 15 percent across 276 companies. Employer plan forecasts for 2027 run from 8.2 to 11.1 percent. Answered by Dick Tracy, a licensed health insurance broker in Buffalo, NY. Open enrollment is open now, and December 15, 2026 is the last day in most states to pick a plan that starts January 1, so the window to do something about your number is short.
I came out of the healthcare side of this business before I ever sold a policy, so there is no gag clause on me. I am licensed in 25 states with 80+ carriers behind me, and I will give you the tips, the tricks, and the traps. The honest version of this question is not just "will premiums go up." It is "how much, in my state, and what can I actually do about it before the window closes." The news stories answer the first half and stop. The second half gets its own section below.
What insurers asked for in 2027
KFF reviewed 2027 rate filings from 276 marketplace insurers across all 50 states and the District of Columbia and found a median proposed increase of 15 percent. That is the second straight year of double digit proposals and the second highest requested change since 2018. The spread was wide: requests ran from minus 1 percent to 54 percent, 63 percent of them landed between 10 and 25 percent, and 51 insurers asked for more than 25 percent.
Insurers told regulators why. Higher prices for health services, general inflation, and labor shortages account for the bulk of it. On top of that, the enhanced premium tax credits expired at the end of 2025, and insurers expect that to make the pool of people who stay enrolled sicker on average, because healthy people are the ones who drop coverage when the price goes up. That second piece is the one that compounds: fewer healthy enrollees means a higher average claim, which means next year's filing goes up again.
What states have actually approved for 2027
Proposed rates are a request. The number that hits your renewal letter is the one the state signs off on, and through September, October and early November the approvals landed one state at a time. Here is where the public record stood on November 12, 2026: all 50 states plus DC are final. The first table holds the 32 states plus DC that were done by October 17. The second holds the 18 that finished after that. Where the regulator published its own statewide average, that is the number in the table. Where it published only approved rates by company, or only the approved filings, the table shows the enrollment-weighted average of those filings, marked with a dagger, and links you to the regulator's own record so you can see the company by company numbers. I would rather label an estimate than dress it up as an official figure.
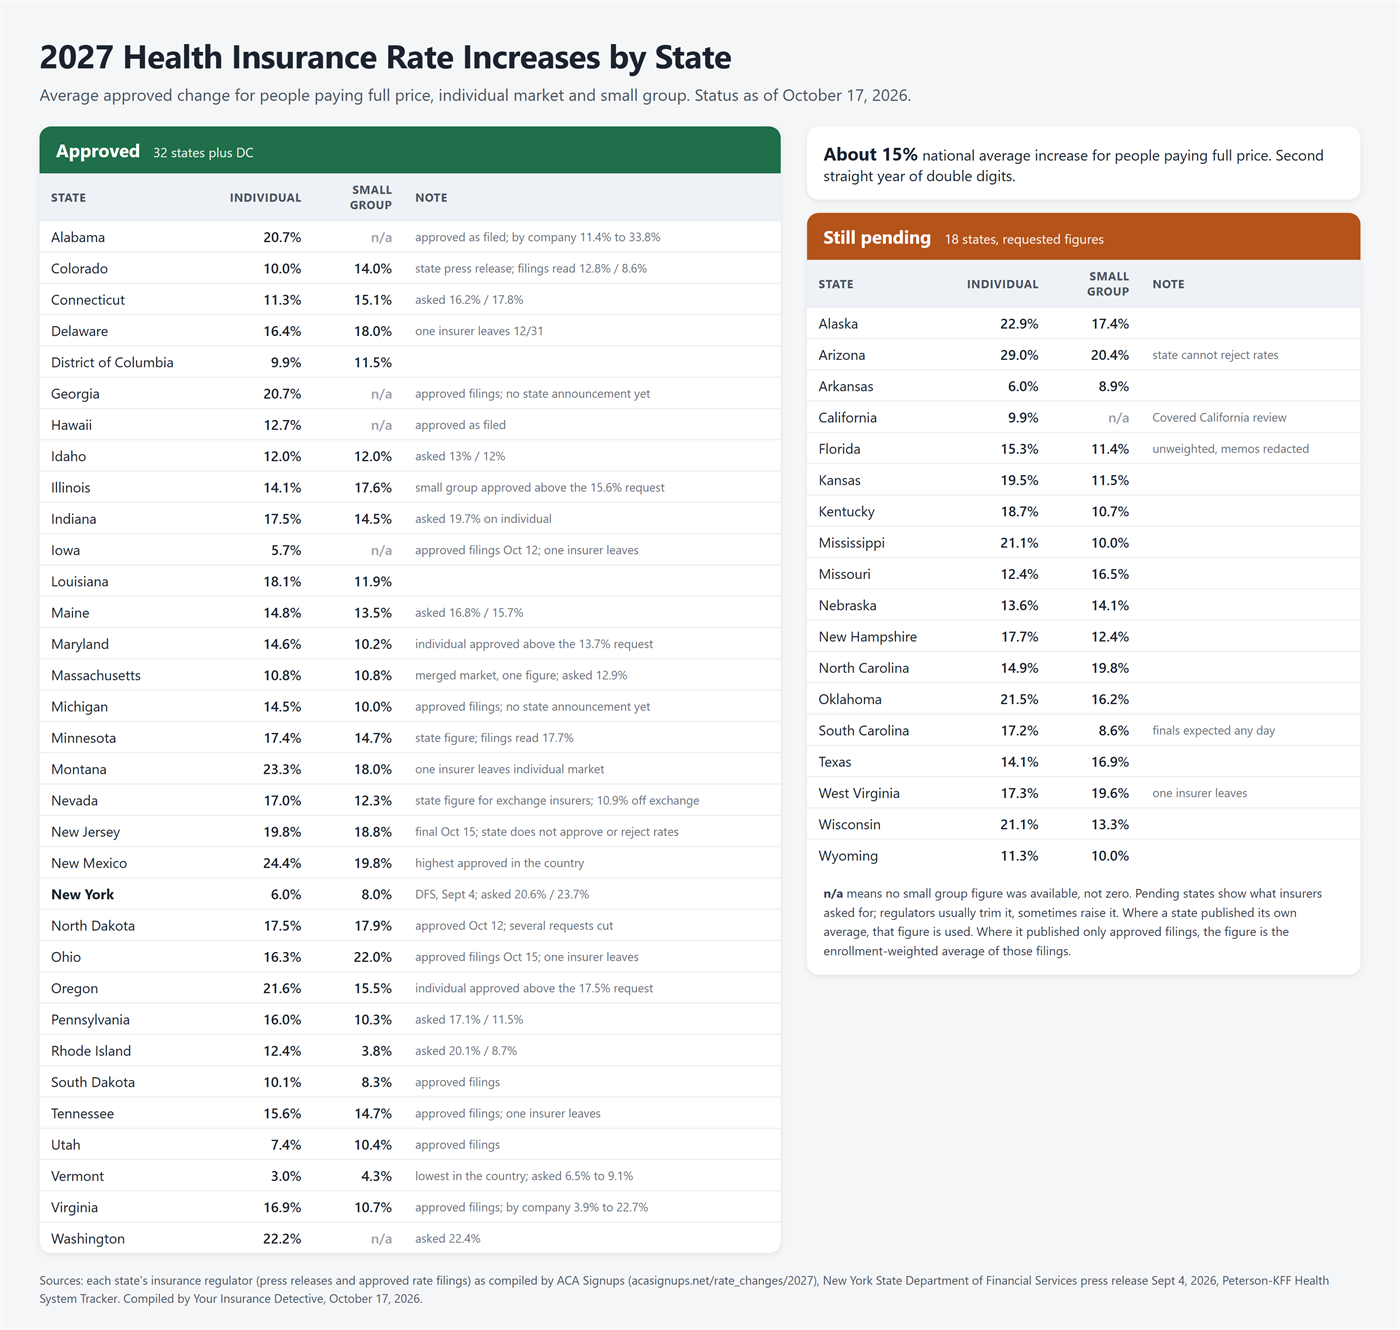
| State | Individual market | Small group | Decided | Source |
|---|---|---|---|---|
| Alabama | 20.7%† | not stated | Sep 3, 2026 | Department of Insurance |
| Colorado | 10.0% | 14.0% | Sep 22, 2026 | Division of Insurance |
| Connecticut | 11.3% | 15.1% | Sep 11, 2026 | Insurance Department |
| Delaware | 16.4%† | 18.0% | Sep 4, 2026 | Department of Insurance |
| District of Columbia | 9.9% | 11.5% | Sep 18, 2026 | Dept. of Insurance, Securities and Banking |
| Georgia | 20.7%† | not stated | filings, no state release yet | Rate filings |
| Hawaii | 12.7%† | not stated | filings, no state release | Insurance Division filings |
| Idaho | 12.0% | 12.0% | Oct 6, 2026 | Department of Insurance |
| Illinois | 14.1% | 17.6% | Sep 16, 2026 | Department of Insurance |
| Indiana | 17.5% | not stated | final, undated | Department of Insurance |
| Iowa | 5.7%† | not stated | filings, Oct 12, 2026 | Insurance Division |
| Louisiana | 18.1%† | 11.9%† | filings, Sep 24, 2026 | Rate filings |
| Maine | 14.8% | 13.5% | Aug 14, 2026 | Bureau of Insurance |
| Maryland | 14.6% | 10.2% | Sep 25, 2026 | Insurance Administration |
| Massachusetts | 10.8% | 10.8% | final table (first approvals Jul 22, 2026 averaged 10.4%) | Division of Insurance (one merged market figure) |
| Michigan | 14.5%† | 10.0%† | filings, no state release yet | Rate filings |
| Minnesota | 17.4% | 14.7%† | Oct 1, 2026 | Department of Commerce |
| Montana | 23.3%† | 18.0%† | filings, no state release | Rate filings |
| Nevada | 17.0% | 12.3%† | Oct 1, 2026 | Division of Insurance (exchange insurers; 10.9% for off-exchange-only insurers) |
| New Jersey | 19.8% | 18.8% | Oct 15, 2026 | Dept. of Banking and Insurance (final filed; the department does not approve or reject on price) |
| New Mexico | 24.4% | 19.8% | Sep 1 and Oct 8, 2026 | Office of Superintendent of Insurance, small group |
| New York | 6.0% | 8.0% | Sep 4, 2026 | Dept. of Financial Services |
| North Dakota | 17.5%† | 17.9%† | Oct 12, 2026 | Insurance Department |
| Ohio | 16.3%† | 22.0%† | filings, Oct 15, 2026 | Rate filings |
| Oregon | 21.6% | 15.5% | Aug 18, 2026 | Division of Financial Regulation |
| Pennsylvania | 15.97% | 10.28% | Sep 18, 2026 | Insurance Department |
| Rhode Island | 12.4% | 3.8% | Sep 29, 2026 | Office of the Health Insurance Commissioner |
| South Dakota | 10.1%† | 8.3%† | filings, no state release yet | Rate filings |
| Tennessee | 15.6%† | 14.7%† | filings, no state release | Rate filings |
| Utah | 7.4%† | 10.4%† | filings, no state release | Insurance Department rate database |
| Vermont | 3.0%† | 4.3%† | Aug 18, 2026 | Green Mountain Care Board |
| Virginia | 3.9% to 22.7% by company | 7.6% to 20.7% by company | Sep 16, 2026 | Bureau of Insurance (no statewide average published) |
| Washington | 22.2% | not stated | Sep 9, 2026 | Office of the Insurance Commissioner |
Most of those came in under the request, and some by a lot. New York insurers asked for 20.6 percent on individual plans and 23.7 percent on small group and were approved at 6.0 and 8.0, which the state put at roughly $1.6 billion kept in the pockets of about 860,000 New Yorkers. Rhode Island cut a 20.1 percent request to 12.4. Connecticut cut 16.2 percent down to 11.3. Pennsylvania trimmed 17.14 percent to 15.97 percent and said it denied $94.7 million in increases it judged unjustified. Indiana brought 19.7 percent down to 17.5. But rate review runs in both directions. Oregon's regulator approved 21.6 percent on the individual market after insurers asked for 17.5, citing enrollment losses and insurer financial results. Maryland approved 14.6 percent against a 13.7 percent request, and Illinois small group finished at 17.6 percent against 15.6. New Jersey's department says plainly that it does not approve or reject filings on price, so its 19.8 percent is final rather than approved. Rate review is not theater, but it is also not a rescue: the direction is still up everywhere.
The last 18 states: what insurers asked for and what came through
These 18 states were still pending in the middle of October. All of them are final now. The first number is what insurers asked for and the second is the final average, so you can see how far the review moved it. By this compilation, nine came in under the request, six came in over it (Arkansas, Nebraska, New Hampshire, South Carolina, Texas and Wisconsin), and three did not move.
| State | Individual, requested | Individual, final | Small group, final |
|---|---|---|---|
| Alaska | 22.9% | 22.5% | 17.4% |
| Arizona | 29.0% | 27.9% | 19.7% |
| Arkansas | 6.0% | 7.6% | 8.9% |
| California | 9.9% | 9.9% | 14.4% (unweighted) |
| Florida | 15.3% | 10.4% | 11.4% (unweighted) |
| Kansas | 19.5% | 19.5% | 12.4% |
| Kentucky | 18.7% | 18.7% | 10.7% |
| Mississippi | 21.1% | 20.2% | 10.0% |
| Missouri | 12.4% | 12.3% | 16.5% |
| Nebraska | 13.6% | 13.8% | 14.1% |
| New Hampshire | 17.7% | 18.9% | 10.3% |
| North Carolina | 14.9% | 14.1% | 18.9% |
| Oklahoma | 21.5% | 21.4% | 16.2% |
| South Carolina | 17.2% | 22.1% | 8.9% |
| Texas | 14.1% | 14.6% | 16.9% |
| West Virginia | 17.3% | 14.9% | 15.8% |
| Wisconsin | 21.1% | 21.7% | 12.5% |
| Wyoming | 11.3% | 11.1% | 10.0% |
Two cautions on those tables. First, California. Covered California announced a statewide average of 9.9 percent on July 21, 2026 as preliminary, and ACA Signups now carries that 9.9 percent as final. I could not find a separate final release from the state as of November 12, 2026, so treat it as the working number. Second, and this is the one that actually bites: a statewide average is not a promise about your plan. Rates are filed by company and by region. In Western New York, where I sit, the approved 2027 changes for the insurers that sell here run from 0 to 12.2 percent on individual plans against that 6.0 percent statewide average. If your letter says a bigger number than the headline, nobody made a mistake. Your insurer came in above the average. I walk through that gap in detail on why your health insurance went up and in the Western New York 2027 rate breakdown.
Why the number on your letter can move more than the rate
Here is where people get blindsided, and it has nothing to do with the approved percentage. The premium is what the plan costs. What you pay is the premium minus whatever help you qualify for. Those are two different numbers, and since the enhanced credits expired at the end of 2025 the second one has been moving faster than the first. The old rule came back for 2026 and it is still in force for 2027: above 400 percent of the federal poverty level, marketplace help stops cold. Not shrinks. Stops. So a household that crosses that line sees a modest approved rate increase turn into a renewal that is hundreds or thousands of dollars a month higher. The math doesn't math, and nobody is going to call and warn you.
If you want your own number instead of an average, run it: the 2026 subsidy calculator shows what help you qualify for at a given income, and the free 2026 subsidy cliff calculator tells you in about a minute which side of the line you are on.
I will give you the straight version of what the marketplace is. It is one tool, and for some people it is the right one. It is also the only place that prices coverage without asking about your health, which matters a great deal to some readers and not at all to others. The trade-offs are real: networks on exchange plans tend to be narrower than what people expect, in community rated states like New York everyone pays the same rate regardless of health so the healthy subsidize the sick, your subsidy is built on an income you have to estimate a year in advance, and if you guess low you pay the difference back at tax time. If you are clearly subsidy eligible and your income is modest, those credits may genuinely be your best deal, and I will tell you so after I look at the numbers. What I will not do is let you assume it is the only door.
If your coverage comes through work
Same wave, different wording. The 2027 employer forecasts published in August and September 2026 run from 8.2 percent to 11.1 percent. Mercer put it at 8.2 percent and called it the largest increase since 2003, while noting that employers estimate 11 percent if they changed nothing to hold cost down. Aon projected 9.5 percent and put average cost above $19,000 per employee. WTW came in at 11.1 percent before plan design changes. Most of that spread is one methodology choice: whether the figure is measured before or after the employer shifts cost onto workers.
Which tells you how it reaches you. An 8 percent plan trend does not show up as an 8 percent payroll deduction. It shows up as a bigger deduction, or a bigger deductible, or a narrower network, or a spouse surcharge, in whatever mix your employer picks at renewal. If your share of a work plan has gotten expensive enough that you are wondering about alternatives, that is a real conversation and the answer depends on whether your plan passes the affordability test. There is a free affordability calculator for that.
What you can actually do before December 15
This is the part the rate stories skip, so here it is in order of what moves the needle.
1. Put the dates in your calendar now. Open enrollment runs November 1, 2026 through January 15, 2027 in most states, and December 15, 2026 is the last day in most states to pick something that starts January 1. New York, New Jersey, and California run through January 31, 2027. The full set of dates and deadlines is on the 2027 open enrollment page.
2. Do not auto renew. This is the cheapest mistake to avoid and the most common one made. Plans get repriced every year and they do not move together. The plan that was the best value for 2026 is frequently not the best value for 2027, sometimes inside the same company's own lineup. Auto renewal is a convenience feature, not a recommendation.
3. Know your subsidy line before you choose anything. Not after. Your modified adjusted gross income for 2027 is what the credit is built on, and if you are anywhere near 400 percent of the federal poverty level you need a real estimate rather than a shrug. Pre-tax retirement contributions and ordinary self-employed deductions lower that countable number, which is a conversation for you and your tax professional, not for me. But know the lever exists, because plenty of people fall off that cliff who did not have to.
4. If you are reasonably healthy and self employed, price the other door. For a lot of my clients the better answer is not a different exchange plan, it is not an exchange plan. In New York, healthy individuals, families, and small businesses can merge into a pre-established ERISA group plan. ERISA is federal law from 1974 and it overrides New York's community rating, so you get group rates, a true PPO on nationwide networks, and a policy that you own rather than your employer. It is a simple compliance step I walk you through. In states with private underwriting, the door is a customized individual plan priced on you instead of on the whole community, which for a healthy household can come in well under an unsubsidized exchange plan. And sometimes the honest answer is that you do not need a group plan at all: I build the plan around the situation, and often that means cost-effective customized individual coverage instead of a one-size-fits-all group policy.
None of those three doors is right for everybody, and anyone who tells you otherwise should worry you. A recent serious diagnosis, for instance, usually points back toward guaranteed-issue marketplace coverage for now, and I will say that out loud even though it is not the answer that pays me. You deserve to see the options side by side before you sign anything.
Common questions about 2027 health insurance premiums
Will health insurance premiums go up in 2027?
Yes, for most people. Marketplace insurers asked for a median increase of 15 percent for 2027 across 276 companies in all 50 states and DC, according to KFF, and KFF's review of the finalized rates found benchmark silver premiums up 13 percent on average. All 50 states plus DC now have final rates, and the individual market averages run from 3.0 percent in Vermont and 6.0 percent in New York up to 27.9 percent in Arizona. If your coverage comes through work, the 2027 forecasts published in August and September 2026 landed between 8.2 percent (Mercer) and 11.1 percent (WTW). Planning on a flat premium is not realistic. Planning on reviewing your options every fall is.
How much are ACA marketplace premiums going up in 2027?
KFF reviewed 2027 rate filings from 276 marketplace insurers across all 50 states and DC and found a median proposed increase of 15 percent, the second straight year of double digit proposals. The requests ranged from minus 1 percent to 54 percent, 63 percent of them fell between 10 and 25 percent, and 51 insurers asked for more than 25 percent. One thing worth knowing: for 2026 the median proposed increase was 18 percent and the median finalized increase came in at 20 percent, so a proposed number is not a ceiling. For 2027, KFF's November 6, 2026 review of the finalized rates found benchmark silver premiums up 13 percent on average: 11 percent in HealthCare.gov states and 16 percent in states that run their own exchange.
Which states have approved their 2027 health insurance rates, and by how much?
As of November 12, 2026, all 50 states plus DC have final 2027 individual market rates. The highest statewide averages are Arizona 27.9 percent, New Mexico 24.4 percent, Montana 23.3 percent, Alaska 22.5 percent, Washington 22.2 percent, and South Carolina 22.1 percent. The lowest are Vermont 3.0 percent, Iowa 5.7 percent, New York 6.0 percent, Utah 7.4 percent, and Arkansas 7.6 percent. Most states approved less than insurers asked for: New York insurers requested 20.6 percent and got 6.0 percent, and Rhode Island cut a 20.1 percent request to 12.4 percent. A few went the other way: Oregon approved 21.6 percent against a 17.5 percent request, and Maryland approved 14.6 percent against 13.7 percent. A statewide average is not a promise about your plan.
Will employer health insurance premiums go up in 2027?
Yes. The 2027 forecasts published in August and September 2026 run from 8.2 percent (Mercer, which called it the largest increase since 2003) to 9.5 percent (Aon, which put average cost above $19,000 per employee) to 11.1 percent (WTW, before plan design changes). Most of that spread is one choice: whether the number is measured before or after the employer shifts cost onto workers. Either way it reaches you as a bigger payroll deduction, a bigger deductible, or both.
What can I actually do if my 2027 premium goes up?
Four things, and the first one is a calendar item. Open enrollment runs November 1, 2026 through January 15, 2027 in most states, and December 15, 2026 is the last day in most states for a January 1 start. Second, do not auto renew: the plan that was priced well for 2026 is often not the one priced well for 2027. Third, check the subsidy line, because what you pay and what the plan costs are two different numbers since the enhanced credits expired at the end of 2025. Fourth, if you are reasonably healthy and self employed, price the private market route next to the renewal before you sign anything. I educate, you decide.
Send me your renewal letter and your income estimate and I will lay the real options side by side: what the renewal costs, what help you qualify for, and what the private market would price you at. No hard sell, ever. I educate, you decide.
Grab a time right here
Pick a slot below and it lands on both our calendars. No phone tag, no hard sell. I educate, you decide.